The infection that keeps coming back has a reason it keeps coming back.
Chronic urinary tract infections persist because their bacteria shelter inside biofilms that antibiotics struggle to penetrate. hi® delivers a patented combination of percussive and vibratory mechanical stimulation deep into the bladder and pelvic floor. This page lays out the rationale, the protocols, and the peer-reviewed science behind the approach.
hi® is a wellness device and makes no medical claims. The techniques here are offered for qualified healthcare providers to consider as a possible non-pharmacologic way to support the therapeutic agents a patient is already using. No claim of benefit or cure is made.*

Antibiotics aren't failing. They're being blocked.
Chronic UTI is increasingly understood as a multifactorial condition: biofilm persistence, incomplete bladder emptying, altered pelvic perfusion, lymphatic stagnation, and neuromuscular dysfunction all play a part. Understanding the loop is the first step to understanding the rationale.
The bacteria behind these infections often build protective biofilms: aggregates embedded in a self-produced extracellular matrix that adheres to bladder and urethral surfaces, shielding the colony from antibiotics and immune cells alike.
So a course of antibiotics ends and symptoms fade, but the sheltered survivors remain. Days or weeks later they multiply, and the infection returns. Each loop of infection, antibiotics, and reinfection raises the odds of antibiotic resistance.
The missing piece is rarely a stronger drug. It's a way to get the drug, the immune system, and fresh perfusion past the shield and into the tissue where the bacteria actually live.
If you can't dissolve the shield, shake it loose.
The core rationale is simple. Percussion and vibration transfer kinetic energy externally, through the body, into the bladder, urethra, and surrounding tissue. The aim is to mechanically perturb the biofilm and move the antibiotic-containing fluid into regions it might not otherwise reach. The detailed science follows further down the page.
Bacteria hide behind a biofilm
The extracellular matrix keeps antibiotics in the urine from reaching the bacteria sheltered beneath it.
Kinetic energy perturbs the matrix
Combined percussion and vibration generate micro-shear forces intended to disrupt biofilm architecture and agitate the surrounding fluid.
The therapy can reach further
With the matrix disturbed and perfusion increased, more bacteria are exposed to the antibiotic already present in the urine and tissue.
Your dentist already relies on this.
Dental plaque is a biofilm. Chemicals alone don't remove it; mechanical disruption through scaling and brushing does. Physically breaking up the matrix has long been the only reliable way to manage it. hi® applies the same principle to the bladder and urethra, externally.
The same physics used in the lungs.
Percussive and vibratory therapy with postural drainage is a standard technique for clearing thick mucus, particularly in cystic fibrosis. The principle of mechanical energy enhancing therapeutic access is well established across multiple fields of medicine, as the science section below details. See the evidence ↓
Dr. Andy Davis on using the protocol during his own chronic UTI.
When a chronic bladder and urinary tract infection became a recurring problem in his own life, Dr. Andy Davis applied the hi® protocols alongside his prescribed therapy. In this conversation he walks through what he did, how he structured each session around the medication in his system, and what the experience was like in practical terms.
For clinically minded viewers, it's a useful window into how the technique fits into a real treatment routine rather than a controlled trial: when he timed sessions, how he worked with a full bladder, and where the percussion and vibration were directed.
Dr. Andy Davis shares his personal, individual experience. His account is anecdotal and is not evidence of efficacy or a treatment recommendation. Outcomes vary, and any use of hi® should be discussed with your own healthcare provider.*
Personal experience using the hi® protocol for chronic UTI
Where the energy goes, and how.
The protocols differ by anatomy. Each technique is applied externally for roughly three to five minutes, with the unit repositioned slightly if held longer than three minutes in one spot. The animations below show how hi® transfers percussion and vibration into the internal pelvic structures, and each set links to the demonstration video. These are overviews; the techniques are taught in full during provider-guided training.
Female Anatomy
3 TechniquesThree external positions target the bladder, urethra, and pelvic floor. Combined percussion and vibration appear to stimulate the whole region and, with the vibratory guide engaged, activate the bulbocavernosus reflex, producing contractions along the urethra. Ideally the bladder is full of antibiotic-containing urine so the tissue is expanded during stimulation.

Lower Abdominal
Placed sideways on the lower abdomen, just above the pelvic bone. Percussion sends compression waves down into the bladder. Many people find a spot that produces a strong urge to urinate; held there, it works the bladder wall directly.

Upper Pelvic
The upper head sits above the pubic symphysis, sending a wave directly over the bladder; the lower head sits below it on the mons pubis, sending a wave through the path of the urethra and urethral sphincter. The blue vibratory guide adds vibration that appears to trigger the bulbocavernosus reflex.

Middle Pelvic
The upper head sits just below the pubic symphysis; the lower head sits at the perineum, above the coccyx. This strongly engages the puborectalis, pubococcygeus, and iliococcygeus muscles while rapidly triggering the bulbocavernosus reflex, with internal contractions that may further increase antibiotic exposure.
Example Routine · Female
- With the bladder partially or fully full, apply lower abdominal stimulation for at least 3 minutes.
- Apply upper pelvic stimulation for at least 3 minutes.
- Apply middle pelvic stimulation for at least 3 minutes.
- Urinate roughly half the bladder volume, then repeat all three techniques.
- Urinate the remaining volume and repeat all three techniques once more. Ideally perform twice daily, morning and evening, or as your provider recommends.
Male Anatomy
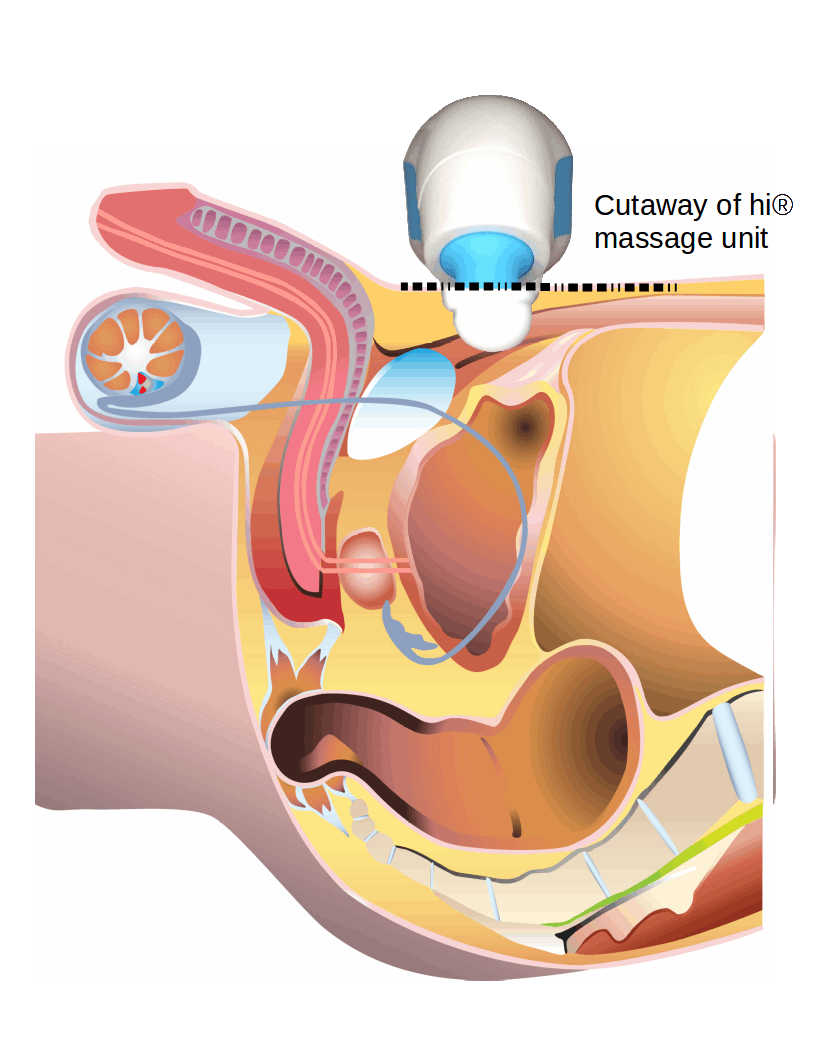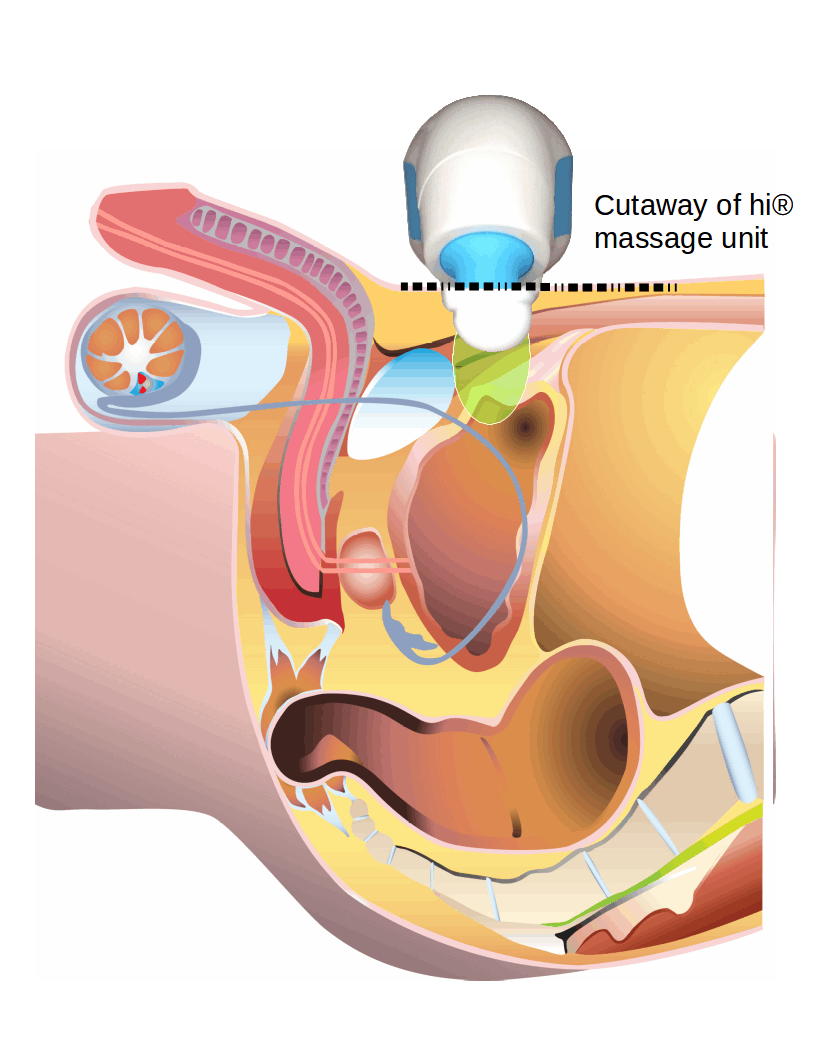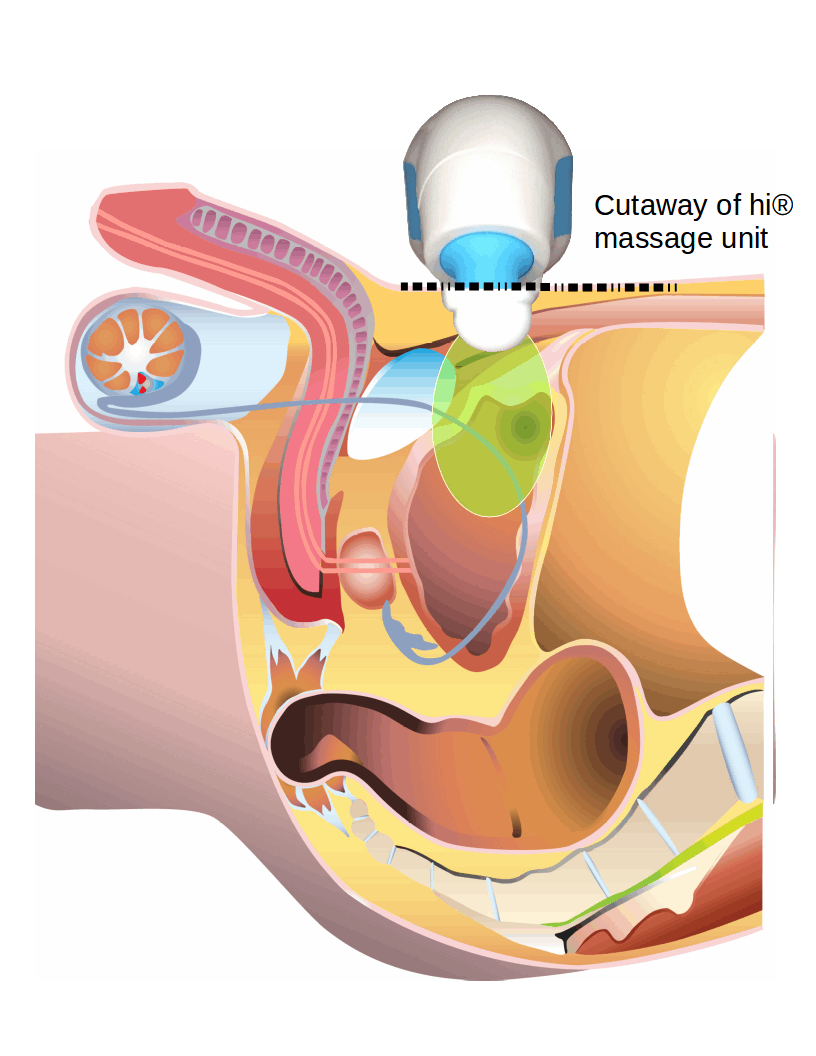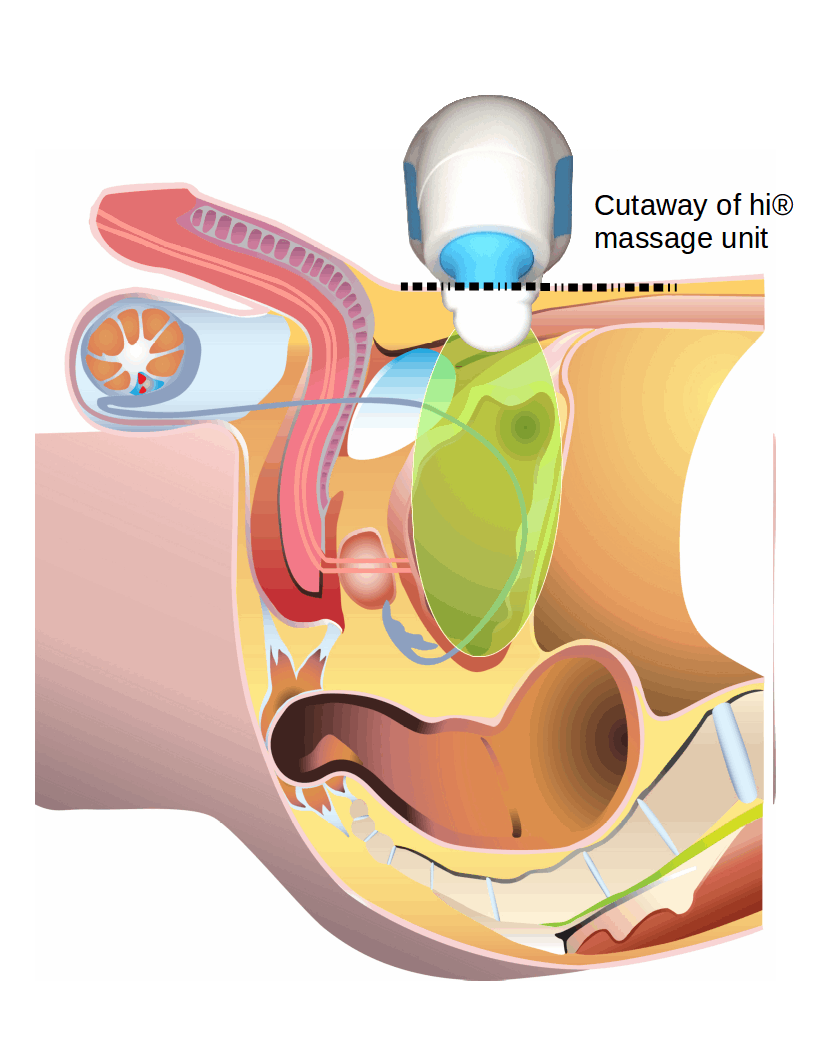
5 TechniquesMale protocols add direct treatment of the urethral path through the penis and the perineal region over the prostate. The goal across all of them is to flush the urethra with the urine-and-antibiotic mixture, then apply vibratory and percussive stimulation along every segment the urethra travels, as well as the prostate.
Lower Abdominal
Held just above the pelvic bone, sending compression waves into the lower abdomen and bladder, ideally with the bladder full of antibiotic-containing urine.

Urethral Vibration
The blue vibratory guide is moved along the path of the urethra from base to glans, on each side, at varying speeds. The aim is to disrupt biofilm and increase contact between the urine-antibiotic mixture and the urethral mucosa.

Urethral Vibration + Percussion
An optional, more vigorous variant combining vibration and percussion along the same urethral path. Introduced carefully and briefly at first, with attention to avoid pinching.

Perineal Vibration
The vibratory guide is applied at the base of the penis behind the testicles, then along the perineum, targeting the urethral segment between the penis and bladder and the prostate region.

Perineal Percussion
An optional, more advanced technique applying percussion across the perineum toward the prostate and the urethral channel at the base of the penis. Requires care with balance and positioning.
Example Routine · Male
- With the bladder partially or fully full, apply lower abdominal stimulation for at least 3 minutes.
- Stand and briefly urinate, then hold the testicles clear and apply vibratory or percussive stimulation of the perineum.
- Urinate again and apply vibratory, or combined vibratory and percussive, stimulation of the urethra in the penis.
- Urinate again and repeat the sequence. Perform at least once daily, or more often while taking antibiotics if your provider recommends.
Some providers also discuss pairing the protocol with D-mannose alongside the prescribed medication, and continuing both for about a month after symptoms resolve. Whether any of this is appropriate is a decision for you and your provider.
Six biologically plausible mechanisms.
Chronic UTI is multifactorial, so the rationale for mechanical stimulation is multifactorial too. Below are six mechanisms by which low-frequency percussive and vibratory stimulation, as delivered by hi®, may support CUTI management, each grounded in peer-reviewed clinical, mechanistic, and translational literature.
Direct clinical studies using hi® specifically are limited. What follows is the converging evidence from adjacent modalities, ultrasound, shockwave, whole-body and local vibration, and percussive therapy, that establishes biological plausibility and motivates formal investigation. Every linked source is peer-reviewed or from an indexed clinical database.
Biofilm Disruption & Enhanced Antibiotic Interaction
Chronic UTIs frequently involve bacterial biofilms, aggregates embedded in a protective extracellular matrix that shields them from antibiotics and immune cells. Mechanical forces such as low-frequency vibration, shockwave, and acoustic cavitation can physically perturb biofilms, reducing density and exposing bacteria to the surrounding fluid. The hypothesis is that repeated percussive stimulation over the bladder and pelvic region generates analogous micro-shear forces that disturb biofilm architecture.
Direct Support From Low-Frequency Bladder Vibration
A 2024 randomized controlled trial of low-frequency bladder vibration (5–10 Hz) in patients with UTIs and neurogenic bladder reported significant reductions in urinary leukocytes and bacterial counts, lower post-void residual volume, increased urine output, and reduced symptoms four weeks after intervention. The frequencies overlap with the percussive range applied by devices like hi®, and the effects were clinically measurable and sustained.
Improved Tissue Perfusion & Blood Flow
Mechanical vibration and percussive stimulation increase local blood flow and microvascular perfusion across multiple human studies, including nitric-oxide-mediated vasodilation. Around the bladder and pelvic tissues, improved perfusion may enhance oxygen and nutrient delivery, immune cell trafficking, and tissue repair, reducing the stagnation that favors bacterial persistence.
Lymphatic Flow & Fluid Drainage
The broader massage and vibration literature indicates mechanical stimulation can enhance lymphatic drainage and fluid transport. A randomized pragmatic trial found low-frequency vibrotherapy added to manual lymphatic drainage significantly outperformed drainage alone. Enhanced lymphatic movement may help clear inflammatory byproducts and bacterial debris from pelvic tissues, lowering local inflammatory burden.
Neuromuscular Function & Tissue Responsiveness
Vibration and percussion influence muscle performance and neuromuscular responsiveness. Intravaginal vibratory stimulation has outperformed electrical stimulation for pelvic-floor strength, and whole-body vibration recruits the pelvic floor via the tonic vibration reflex. Better neuromuscular function may support more complete bladder emptying, reducing residual urine, a known risk factor for infection, and easing pelvic tension that creates stagnant, growth-favorable conditions.
Nervous System Modulation & Comfort
Mechanical stimulation reduces perceived tissue stiffness and alters sensory experience. Cutaneous vibration produces reliable analgesia consistent with gate-control theory, and changes peripheral and central afferent processing. While not antimicrobial, improved comfort and reduced muscle tension can meaningfully improve adherence to a daily protocol, which in turn supports circulation, lymphatic flow, and immune function.
Evidence summary & honest limitations
The closest direct clinical support is the 2024 bladder-vibration RCT (5–10 Hz) in neurogenic bladder, which improved urinary leukocytes, bacterial counts, and post-void residual. Around it sits substantial peer-reviewed literature on mechanical and ultrasonic biofilm disruption, vibration-mediated perfusion and nitric oxide, lymphatic augmentation, tonic-vibration-reflex activation of the pelvic floor, and vibratory analgesia.
For several of the six mechanisms, the evidence is analogous, drawn from ultrasound, shockwave, or whole-body vibration, rather than from handheld percussive devices applied externally to the lower abdomen and urethra. Randomized clinical data specific to hi® are limited. These mechanisms are extrapolated from related literature and define a clear, fundable research agenda.
// No claim of medical benefit or cure is made. This material is for qualified healthcare providers to evaluate.

Engineered for the pelvis, not adapted to it.
A standard percussion massager is built for shoulders and quads. hi® was designed from the start for pelvic applications, combining two independently controlled forms of stimulation that single-modality devices cannot produce together.
A powerful tool deserves honest caution.
hi® is a strong percussive and vibratory system. Like any such device, there are situations where it should not be used, and that judgment belongs with you and your healthcare provider, especially when an active infection is involved.
If you're a patient, please review this approach with your provider before trying it, to confirm it's appropriate for your situation. If you're a provider, we're glad to share technical details and experiences, or refer you to professionals familiar with this approach. Contact us with questions →
hi® should generally not be used if you:
- Are pregnant or think you might be
- Have deep vein thrombosis, a clotting disorder, or artificial joints
- Have abdominal or pelvic mesh, an implant, or surgery within the past 6 months
- Have any cancer, unknown tumors, open wounds, or active bruising
- Have a possible fistula between bowel and bladder
- Have high blood pressure your provider has cautioned you about
- Are not in good enough physical health for a vigorous massage
A study is underway. You can be part of what's next.
The CUTI research trial is currently running. If you'd like to be considered for a future trial, or you're a healthcare provider interested in learning more about these protocols and the evidence behind them, we'd love to hear from you.